
Do you know the rules for differentiating Pleural Effusion (PE) from Pericardial Effusion (PCE)?
It is important to perform a complete Global FAST® POCUS for best assessment of your patients. The FASTVet rules for accurately differentiating pleural effusion (PE) from pericardial effusion (PCE) on TFAST® include the following:
For a Downloadable reference chart, here is the link: FASTVet_TFAST_PE_vs_PCE_Rules Reference Chart 2026!
- Always image the heart in its entirety. Use the bright (hyperechoic) pericardium in the far field as a landmark. Our imaging mantra is: “Center the heart and clearly get it off the bottom of the screen.” Maintain adequate depth so the entire heart and surrounding structures are visible.
- Understand the characteristic appearance of PCE versus PE.
- PCE is contained within the pericardial sac and therefore typically has a rounded appearance surrounding the heart.
- PE is not contained by the pericardial sac. It is free to move and may form triangular or angular collections adjacent to the heart.
- Look for PE using several characteristic findings. PE may be identified as:
- Wafting fluid at the Diaphragmatico-Hepatic (DH) View.
- Triangular collections adjacent to, but separate from, the heart when following the heart-imaging mantra.
- Small-volume fluid cranial or caudal to the heart, including evaluation for the “Curtain Sign” of PE.
- Recognize PCE as fluid contained within the pericardial sac. Because PCE surrounds the heart, it often has a rounded appearance. Several imaging strategies can help prevent mistaking the crescent-shaped right ventricle for effusion:
- Image toward the muscular apex of the heart, where it is less likely that a cardiac chamber—particularly the crescent-shaped right ventricle or left auricular appendage—will be mistaken for PE or PCE.
- Look for the “Racetrack Sign” of PCE at the FAST Diaphragmatico-Hepatic (DH) View. This finding is nearly 100% specific and sensitive for clinically relevant PCE.
- Look for the “Bull’s Eye Sign” at the right TFAST® Pericardial Site.
- Obtain a long-axis 4-chamber view whenever possible. When all four cardiac chambers are clearly identified, PE or PCE can be recognized as fluid located outside the cardiac chambers.
- Do NOT diagnose PCE solely from a right-sided TFAST® Pericardial Site left ventricular short-axis (SAx) view, unless the image is obtained at the “Bull’s Eye” SAx level. At other SAx levels, it is too easy to mistake the crescent-shaped right ventricle for PE or PCE, particularly in distressed patients.
- Save cine clips liberally, especially in distressed cats. Capturing video clips allows the images to be reviewed after the patient has been placed in oxygen, reducing the need for prolonged or repeated image acquisition. Our mantra is: “Get your images by saving, saving, saving; then place the cat in oxygen and return to review the captured images.”
FASTVet® Quick Rules
PE → Think “FREE”
- Free/uncontained fluid
- Runs or triangulates around the heart
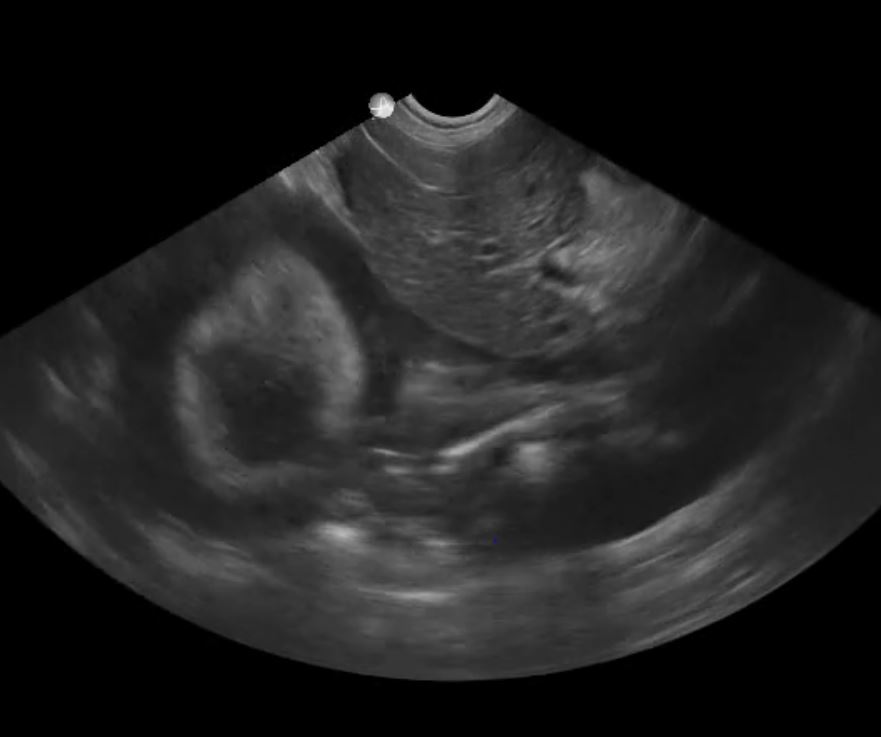
RACETRACK sign of PCE at the DH View (AFAST and TFAST include this view)
- Evaluate cranial and caudal to the heart
- Effusion may waft at the DH View
PCE → Think “CONTAINED”
- Rounded fluid within the pericardial sac
- Racetrack Sign at the DH View
- Bull’s Eye Sign at the right TFAST® Pericardial Site
- Confirm using the muscular apex and long-axis 4-chamber view
- Avoid diagnosing PCE from an isolated LV SAx view
Material copywrite by FASTVet.com 2026